

Connecting Science to Practice
As hematopoietic stem cell transplant (HSCT) data continue to be studied and new agents for graft-versus-host disease (GVHD) prevention emerge, changes to day-to-day practice must be reevaluated and reassessed. This study aimed to bridge the gap between previous data for posttransplant cyclophosphamide use for GVHD prophylaxis and how it correlates to early and late CMV reactivation. Assessing this gap will help cytomegalovirus (CMV) prophylaxis practices continue to evolve, with the duration of use of letermovir to appropriately prevent CMV reactivation in post-HSCT patients.
Cytomegalovirus (CMV) remains one of the most common infections in patients receiving an allogeneic hematopoietic stem cell transplant (HSCT).1 The population at highest risk for CMV reactivation after HSCT is seropositive recipients of seronegative donors (CMV R+/D-), followed by seropositive recipients of seropositive donors (CMV R+/D+) at moderate risk; seronegative recipients of seropositive donors (CMV R-/D+) at low risk. Seronegative recipients of seronegative donors (CMV R-/D-) have rare cases of CMV reactivation.2-4 The risk factors for CMV reactivation beyond day 100 include related or unrelated donors with ≥1 mismatch at human leukocyte antigen (HLA)-A, HLA-B, HLA-C, or HLA-DR; having a haploidentical donor; receiving umbilical cord blood as a stem cell source; lymphopenia defined as <100 lymphocytes/mm3; CMV infection before day 100; graft-versus-host disease (GVHD) requiring treatment with high-dose prednisone (>0.5 mg/kg daily prednisone or its equivalent); the absence of CMV-specific T-cell immunity (if measured); and the receipt of antithymocyte globulin (ATG) or any other T-cell–depleting therapy in a conditioning regimen, T-cell–depleted stem cells, or posttransplant cyclophosphamide as a GVHD prophylaxis strategy.5,6
Letermovir is an antiviral agent that binds to components of the CMV terminase complex (UL51, UL56, or both), thereby inhibiting CMV replication.1 Letermovir was FDA-approved for prophylaxis in CMV-seropositive allogeneic HSCT recipients through day 100 (week 14) in 2017.1 Although the registration study for letermovir conducted by Marty and colleagues showed that the incidence of CMV reactivation increased significantly between week 14 and week 24, the risk for CMV-related adverse events (AEs) beyond 14 weeks remains controversial.1 Their study showed that fewer patients in the letermovir group than in the placebo group had clinically significant CMV (CS-CMV) infections by week 24 after transplantation (122 of 325 patients [37.5%] vs 103 of 170 [60.6%]; P<.0001).1
Liu and colleagues conducted a retrospective cohort study of 333 CMV R+ or CMV D+ patients after an allogeneic HSCT.7 This study analyzed the incidence of CS-CMV with and without the use of letermovir for CMV prophylaxis to identify evidence that points to the use of letermovir past day 100.7 The primary end point of CS-CMV at day 180 was 19.46% with letermovir and 39.13% without letermovir (P<.0001).7 The secondary end points included day 100 CS-CMV (8.1% with letermovir and 34.8% without letermovir; P<.0001) and day 365 CS-CMV (24.8% with letermovir and 41.3% without letermovir; P=.001).7 A multivariate analysis of CMV-related mortality demonstrated benefit with letermovir use in days 0 to 99 and worsening during day 180 to day 364 after letermovir was stopped.7 The standard at Geisinger Medical Center allowed provider-driven use of letermovir extending beyond day 100 before the FDA label was updated based on studies reviewed below.
A study by Bansal and colleagues investigated treatment with letermovir past day 100 for patients with acute or chronic GVHD, because the presence of GVHD requiring treatment with either systemic or topical corticosteroids is a risk factor for CMV reactivation.6 Although the inclusion criteria did not state steroid use, all patients in this trial received systemic or topical steroids. Their study’s results showed that extended-duration letermovir was efficacious in preventing CS-CMV in patients with GVHD, and they observed the confirmatory results of late (past day 100) CMV reactivation after the discontinuation of letermovir,6 as seen in the study by Marty and colleagues.1 The primary end point results in Bansal and colleagues’ study suggest that a possible approach to the prevention of CMV reactivation would be to restart letermovir treatment at the time of the GVHD flare.6
Posttransplant cyclophosphamide poses a potential increased risk for CMV reactivation through its T-cell depletion mechanism.8 Posttransplant cyclophosphamide is being used more frequently, with emerging data across variously matched donors (ie, haploidentical, mismatched, and matched donors) that was based on the BMT CTN 1703 study that compared a posttransplant cyclophosphamide-based regimen against the historical standard-of-care tacrolimus/methotrexate combination for GVHD prophylaxis.9 This increased utilization of posttransplant cyclophosphamide can potentially increase the risk for CMV reactivation. Goldsmith and colleagues analyzed the effect of graft source and posttransplant cyclophosphamide treatment on the incidence of CMV infection, and the effects of serostatus and CMV-related AEs on transplant outcomes.8 Their study included patients who received stem cells from the following: a haploidentical donor and received posttransplant cyclophosphamide; a matched related donor (MRD) and received posttransplant cyclophosphamide; and an MRD who received a calcineurin inhibitor–based prophylaxis. This study showed that the cumulative incidences of CMV reactivation (denoted as CMV DNAemia) by day 180 were 42%, 37%, and 23%, respectively (P<.001).8 Ultimately, Goldsmith and colleagues concluded that posttransplant cyclophosphamide treatment, regardless of the donor type, is associated with a higher incidence of CMV infection versus not receiving posttransplant cyclophosphamide, augmenting the risk for CMV seropositivity.8
A phase 3 trial evaluated extending CMV prophylaxis with letermovir from 100 days to 200 days after an allogeneic HSCT for additional benefit compared with placebo in patients at high risk for CS-CMV beyond 100 days after HSCT.10 The risk factors included in this high-risk category were donor relatedness and the degree of matching; stem cell source; treatment with T-cell–depleted grafts, ATG, or alemtuzumab; and GVHD or other conditions necessitating steroid use before randomization.10 The use of posttransplant cyclophosphamide for the evaluation of high risk for late CS-CMV was not collected. This study met its primary end point of benefit by extending letermovir use to day 200, observing that CS-CMV from day 100 through day 200 after HSCT was lower in the letermovir arm than in the placebo arm (3% vs 19%, respectively; 1-sided P=.0005). The safety profiles were similar between the letermovir and placebo groups.10
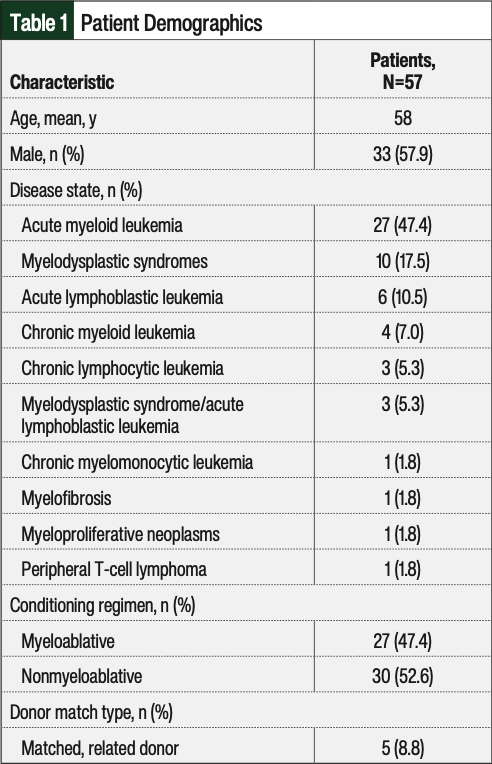
Currently at the Geisinger Medical Center where our study took place, the standard of care for GVHD prevention is cyclosporine with posttransplant cyclophosphamide after allogeneic HSCT. This GVHD prophylaxis regimen increases the risk for CMV-related AEs in patients at this institution. This study aims to evaluate the occurrence of CMV-related AEs and to determine if they are occurring in patients with seropositive donors because of the increased risk with posttransplant cyclophosphamide and if an extended duration of letermovir treatment provides additional benefit.
The study end points include the difference in the occurrence of CMV-related AEs for CMV D+ versus CMV R+ allogeneic HSCT patients; patients having posttransplant cyclophosphamide as GVHD prophylaxis or letermovir prophylaxis compared with those who did not; and the duration of letermovir prophylaxis up to day 100 compared with beyond day 100.
Methods
This study is a retrospective, single-center cohort study that took place at Geisinger Medical Center, an academic medical center, in Danville, PA. The data were collected from electronic health records between June 1, 2013, and June 30, 2023. The study’s inclusion criteria were age ≥18 years, CMV seropositivity from the recipient, donor, or both, and receiving an allogeneic HSCT. The study’s exclusion criterion was not having post-HSCT care managed by the study’s site institution.
A CMV-related AE encompasses either CMV reactivation or CS-CMV. CMV reactivation is defined as 2 consecutive CMV levels of ≥150 copies/mL within 3 to 7 days of one another per the institution’s standard of practice. CS-CMV is defined as CMV detected from an organ system by biopsy or other invasive procedure with sufficient sensitivity and specificity in combination with the signs and/or symptoms of organ disease, or provider-determined CS-CMV. The duration of letermovir treatment was collected individually and categorically among 3 groups: shorter than day 95, day 95 to day 105 (100 ± 5 days), and longer than day 105. These categories of letermovir duration were used to capture the patients who discontinued treatment with letermovir near day 100, but not precisely at day 100.
An analysis of the outcomes involving the descriptive data, such as the difference in the number of patients in various end points that have CMV-related AEs, was done using a chi-square test or Fisher’s exact test. Parametric versus nonparametric analysis was conducted for the quantitative subgroup analysis variables.
Results
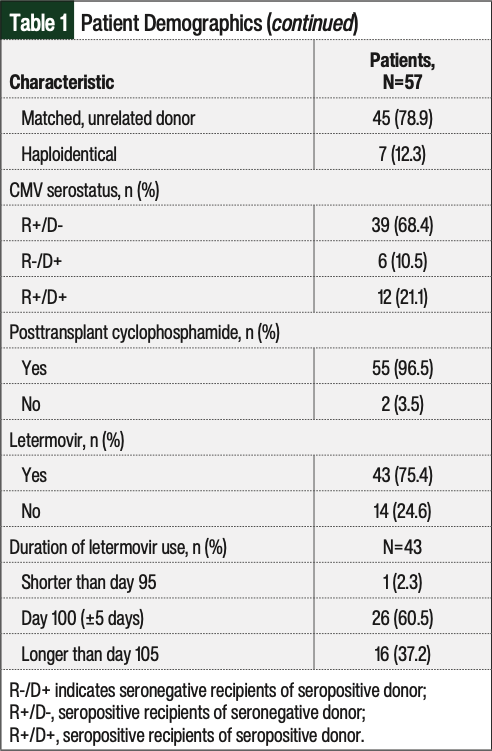
There were 57 patients who met the study’s inclusion criteria. Table 1 shows that most (47.4%) patients had acute myeloid leukemia before having an allogeneic HSCT, followed by myelodysplastic syndrome (17.5%) and acute lymphoblastic leukemia (10.5%). A total of 68.4% of patients were CMV R+/D-, followed by 21.1% being CMV R+/D+ and 10.5% being CMV R-/D+. There was a mix of donor types, including 8.8% MRD, 12.3% haploidentical, and 78.9% a matched unrelated donor.
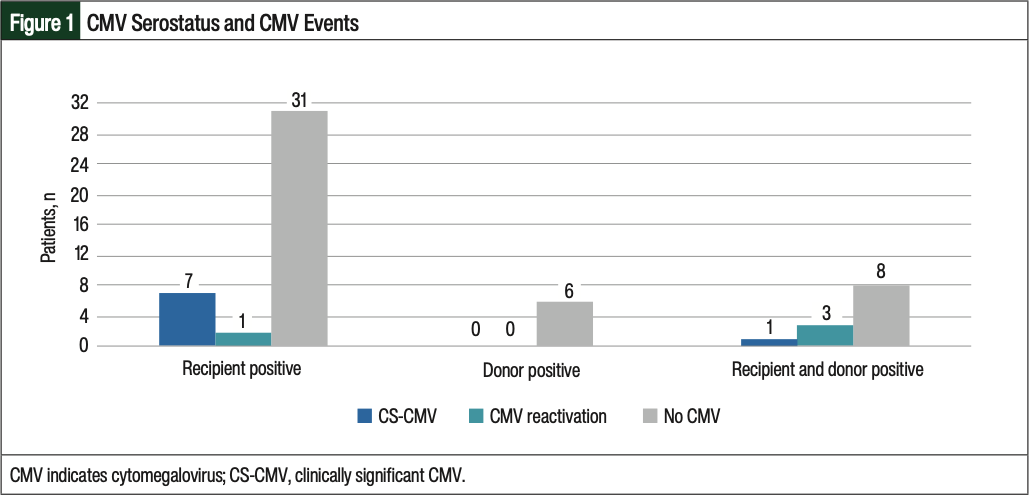
Of the 57 study patients, 12 (21%) had a CMV-related AE, which included 4 patients with CMV reactivation and 8 patients with CS-CMV. No CMV R-/D+ patients had CMV-related AEs in this study (Figure 1). When stratified for all 3 CMV-positive serotypes against CMV reactivation, CS-CMV, and no CMV, there were no significant between-group differences (P=.11). When analyzing only CMV reactivation, the CMV R+/D+ patients (25%) were significantly more likely to have CMV reactivation than the CMV R+/D- (2.5%) or CMV R-/D+ patients (0%; P=.049). The incidence of CMV reactivation was also significant when comparing CMV R+/D+ patients with only CMV R+/D- patients (P=.036).
The secondary outcomes are summarized in Table 2. There was no statistical significance with interventions (posttransplant cyclophosphamide and letermovir, along with the duration of letermovir use) relevant to CMV-related AEs. A total of 55 (96.5%) patients received posttransplant cyclophosphamide as part of a GVHD prophylaxis regimen. Of the 2 patients who did not receive posttransplant cyclophosphamide, 1 had CS-CMV and the other did not have a CMV-related AE. Of the patients who received posttransplant cyclophosphamide, 11 (24.4%) had a CMV-related AE, of whom 7 (12.7%) had CS-CMV and 4 (7.3%) had CMV reactivation. Posttransplant cyclophosphamide resulted in CMV-related AEs compared with the absence of posttransplant cyclophosphamide which, was not statistically significant (P=.38).
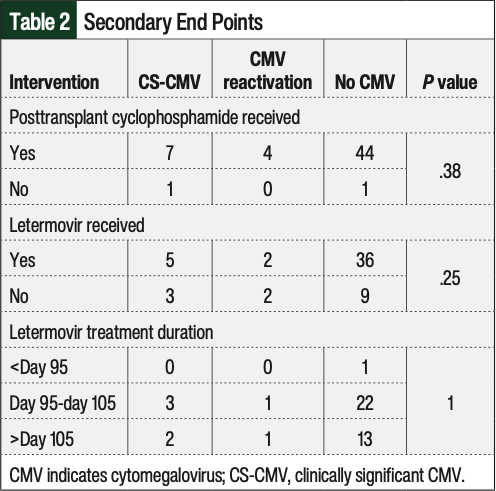
Letermovir prophylaxis was received by approximately 75% of all patients in this study. The reasons for the absence of letermovir prophylaxis included a timeline before approval and the adoption of use at the study site (43%), the CMV donor was seropositive only and therefore at low risk of reactivation (43%), or the reason was unspecified (14%). Receiving letermovir for CMV prophylaxis did not lead to significantly lower rates of CMV-related AEs compared with not receiving letermovir (P=.25); however, 5 (35.7%) patients who did not receive letermovir had a CMV-related AE compared with 7 (16.3%) patients who did receive letermovir. For most of the patients who received letermovir, prophylaxis started on day 9 per our institutional protocol. There were 2 patient outliers who started prophylaxis on day 10 and on day 24, neither of whom had a CMV-related AE despite deviation from the protocol.
The duration of letermovir use ranged from completing therapy at day 92 to day 202, with 16 (28%) patients in the longer-duration group (past day 105).
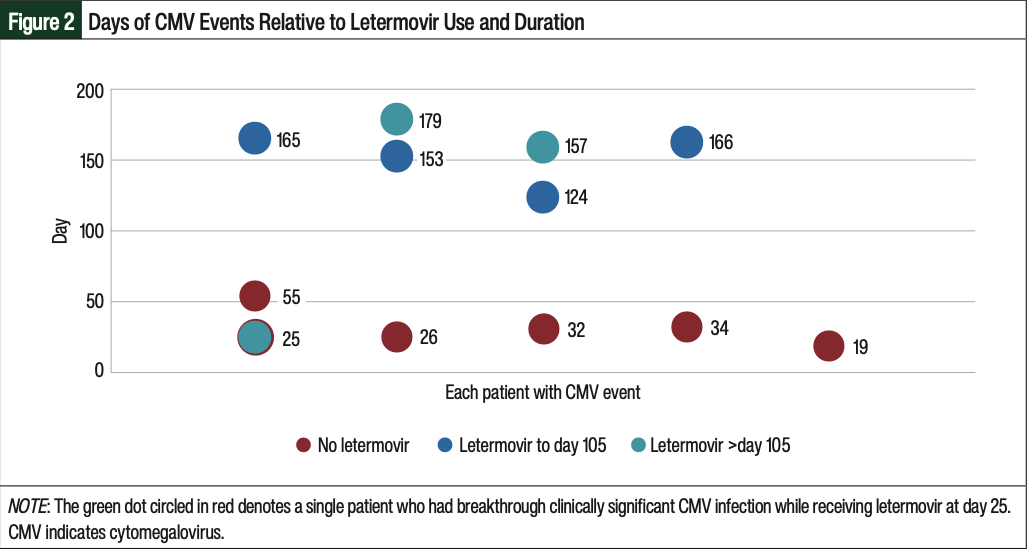
The median last day of letermovir prophylaxis was day 102 in the day 95 to day 105 subgroup, and day 129 in the past day 105 subgroup. A total of 4 (15.4%) patients who received letermovir up to day 105 had a CMV-related AE, whereas 4 (18.8%) patients who received letermovir past day 105 had a CMV-related AE. There was no statistical difference for the duration of letermovir use in correlation to CMV reactivation and CS-CMV (P=1.00).
Figure 2 shows the possibility that the longer letermovir was received, the later CMV-related AEs occurred after allogeneic HSCT (average CMV-related AE on day 152 in the day 95-105 subgroup vs day 168 in the >day 105 subgroup). However, when analyzed through a Pearson correlation, there was only a weak positive correlation between a longer duration of letermovir use and later CMV-related AEs with CS-CMV, not for CMV reactivation or CMV-related AEs as a whole. In patients who received letermovir, CS-CMV and CMV reactivation occurred at an average of 44 days and 54 days, respectively, from the discontinuation of letermovir treatment.
Discussion
Despite all CMV R-/D+ patients receiving posttransplant cyclophosphamide for GVHD prophylaxis and not receiving letermovir prophylaxis, there were no CMV-related AEs within this subgroup, which is consistent with previous studies that did not include posttransplant cyclophosphamide for GVHD prophylaxis.2-4 Inversely, CMV R+/D+ patients were more likely to have CMV reactivation than patients who were CMV R+/D- or CMV R-/D+ in this study, which differs from historical data of risk stratification based on CMV-positive serology.2-4 These data also suggest that the longer letermovir was received, the later CSCMV occurred from allogeneic HSCT, although there was no decrease in the rate of CMV-related AEs.
Limitations
This study was limited by its small population size leading to a lack of power, which negates the statistically significant value found, and by its lack of population that did not receive posttransplant cyclophosphamide, which impacts the comparator group analysis. Other limitations include that CS-CMV prompting treatment was determined by the provider in all cases because they lacked a biopsy-driven diagnosis, other potential overlapping CMV reactivation–related risk factors (eg, ATG use) were not being assessed within this study, the presence of GVHD, and steroid use. Another limitation was the median number of patients in the arm that received extended treatment with letermovir only received letermovir until day 129 due to the timeline of practice change with extending the duration of use. Also, there was difficulty receiving insurance authorization for letermovir use past day 100 because this study’s time frame ended before the prescribing information for letermovir was updated for prophylaxis extension to day 200 in patients with a high risk for CMV-related AEs past 100 days after allogeneic HSCT.
Conclusion
These results support the need for further studies with a larger sample size in patients at high risk for late CMV-related AEs to assess if the risk is indeed higher in CMV R+/D+ patients than in CMV R+/D- patients, because this finding differs from previous studies. Future studies are also warranted with a higher number of patients in comparator groups (no posttransplant cyclophosphamide and longer duration of letermovir treatment) to investigate if a longer duration of letermovir reduces the occurrence of CMV-related AEs in patients receiving posttransplant cyclophosphamide compared with those who do not.
Although posttransplant cyclophosphamide was not included as a risk factor for late CMV reactivation in the letermovir extension study that granted the approval of this duration, extending letermovir use to day 200 for all patients receiving posttransplant cyclophosphamide should be recommended considering the positive safety data compared with placebo and the otherwise known correlation of posttransplant cyclophosphamide with CMV-related AEs.
Author Disclosure Statement
Dr Knauss and Dr Hua have no conflicts of interest to report. Dr Straining, at the time the research was conducted and the manuscript prepared, was affiliated with Geisinger Medical Center, Pharmacy, Danville, PA. Dr Straining is now employed by Novartis Pharmaceuticals Corporation. The research reported here was completed before the author’s employment with Novartis, and Novartis had no role in the conception, design, execution, analysis, or reporting of this work.
References
- Marty FM, Ljungman P, Chemaly RF, et al. Letermovir prophylaxis for cytomegalovirus in hematopoietic-cell transplantation. N Engl J Med. 2017;377:2433-2444. doi:10.1056/NEJMoa1706640
- Teira P, Battiwalla M, Ramanathan M, et al. Early cytomegalovirus reactivation remains associated with increased transplant related mortality in the current era: a CIBMTR analysis. Blood. 2016;127:2427-2438. doi:10. 1182/blood-2015-11-679639
- Ganepola S, Gentilini C, Hilbers U, et al. Patients at high risk for CMV infection and disease show delayed CD8+ T-cell immune recovery after allogeneic stem cell transplantation. Bone Marrow Transplant. 2007;39:293-299. doi:10.1038/sj.bmt.1705585
- Schmidt-Hieber M, Labopin M, Beelen D, et al. CMV serostatus still has an important prognostic impact in de novo acute leukemia patients after allogeneic stem cell transplantation: a report from the Acute Leukemia Working Party of EBMT. Blood. 2013;122:3359-3364. doi:10.1182/blood2013-05-499830
- Johnsrud JJ, Nguyen IT, Domingo W, et al. The changing impact of cytomegalovirus among hematopoietic cell transplant recipients during the past decade: a single institutional cohort study. Transpl Infect Dis.2022;24:e13825. doi:10.1111/tid.13825
- Bansal R, Gordillo CA, Abramova R, et al. Extended letermovir administration, beyond day 100, is effective for CMV prophylaxis in patients with graft versus host disease. Transpl Infect Dis. 2021;23:e13487. doi:10.1111/ tid.13487
- Liu LW, Yn A, Gao F, et al. Letermovir discontinuation at day 100 after allogeneic stem cell transplant is associated with increased CMV-related mortality. Transplant Cell Ther. 2022;28:510.e1-510.e9. doi:10.1016/j. jtct.2022.05.020
- Goldsmith SR, Abid MB, Auletta JJ, et al. Posttransplant cyclophosphamide is associated with increased cytomegalovirus infection: a CIBMTR analysis. Blood. 2021;137:3291-3305. doi:10.1182/blood.2020009362
- Bolaños-Meade J, Hamadani M, Wu J, et al. Post-transplantation cyclophosphamide-based graft-versus-host disease prophylaxis. N Engl J Med. 2023;388:2338-2348. doi:10.1056/NEJMoa2215943
- Russo D, Schmitt M, Pilorge S, et al. Efficacy and safety of extended duration letermovir prophylaxis in recipients of haematopoietic stem-cell transplantation at risk of cytomegalovirus infection: a multicentre, randomised, double-blind, placebo-controlled, phase 3 trial. Lancet Haematol. 2024;11:e127-e135. doi:10.1016/S2352-3026(23)00344-7